
Our Latest Thoughts + Research
-

FEATURED ARTICLE
ASC or HOPD? Know the Numbers Before You Build
|
Read more: ASC or HOPD? Know the Numbers Before You BuildThe outpatient surgery shift is creating new choices for health systems. The opportunity is not simply to move cases to a lower-cost setting, but to use that shift to increase throughput, grow revenue, optimize scarce resources, and get more performance from the assets already in place.
Outpatient surgery has been shifting for years, but the speed, scale, and economics of that shift are changing rapidly. Clinical advances are allowing increasingly complex procedures to move outside the traditional inpatient environment. Payers are increasingly focused on lower-cost sites of care, physicians have more choices about where they practice, and patients are more exposed to differences in cost. At the same time, health systems are trying to grow while facing workforce shortages, constrained capital, and continued pressure to improve access, throughput, and margin.
CMS has added even more momentum to this shift. For calendar year 2026, CMS added 289 procedures to the Ambulatory Surgical Center Covered Procedures List (ASC CPL), along with 271 codes removed from the inpatient-only list. CMS described the changes as providing physicians with greater flexibility to exercise clinical judgment while expanding patients’ choice of care settings. (https://www.cms.gov/newsroom/fact-sheets/calendar-year-2026-hospital-outpatient-prospective-payment-system-opps-ambulatory-surgical-center)
For healthcare leaders, this creates two interconnected decisions. The first is determining where care should be delivered—ASC, HOPD, or hospital. The second is determining how those settings should work together to maximize throughput, revenue, staff, equipment, and existing resources without unnecessary duplication. Getting the first decision wrong can result in millions of dollars invested in the wrong model. Getting the second wrong can result in something equally problematic: building a lower-cost site of care that contributes to a higher-cost health system.
The Economics Are Significant, but They Don’t Tell the Whole Story
The financial differences between ASCs and HOPDs are substantial. A 2026 analysis by KNG Health Consulting for the Ambulatory Surgery Center Association found that in 2024, Medicare paid ASCs, on average, approximately 62% of HOPD rates for the same procedures. From 2019 through 2024, procedures performed in ASCs rather than HOPDs generated an estimated $27.9 billion in Medicare fee-for-service savings, and the analysis projects another $84.8 billion in savings between 2025 and 2034.
Those numbers make a compelling case for lower-cost sites of care, but they should not lead health systems to conclude that an ASC is automatically the right answer. The economics for the health system are more complex. Leaders need to understand reimbursement and contribution margin, but also case mix, clinical complexity, payer mix, physician alignment, patient geography, market growth, regulatory requirements, workforce availability, and the capacity that already exists across the enterprise.
The migration opportunity also varies dramatically by service line. In 2023, more than 70% of eligible eye and ocular procedures were already being performed in ASCs among Medicare populations. Digestive procedures were approximately 40%, while musculoskeletal procedures were still around 19% and cardiovascular procedures approximately 9%. Yet cardiovascular ASC savings are projected to increase 302% between 2025 and 2034, illustrating how quickly the opportunity can change as procedures migrate.
Health systems therefore cannot plan tomorrow’s surgical infrastructure around today’s case mix. They need to understand what is likely to move next, which patients are appropriate for each setting, and what those shifts mean financially and operationally across the entire enterprise.

The First Decision: ASC or HOPD?
The ASC-versus-HOPD decision should begin with the operating and financial strategy, not with a building. An ASC may provide a lower-cost, highly focused environment for appropriate procedures. An HOPD may offer advantages when patients require closer integration with hospital resources, when payer economics favor that model, or when shared services and existing infrastructure create greater enterprise value. In some markets, physician alignment or ownership structures may heavily influence the strategy. In others, regulation may constrain the available choices.
That regulatory landscape is not uniform. Becker’s ASC Review reports that 35 states and Washington, D.C. maintain some form of Certificate-of-Need law. While several states have moved toward loosening restrictions, others have maintained or introduced licensing, assessment, and regulatory hurdles that can affect ASC development. (https://www.beckersasc.com/asc-news/the-states-quietly-making-it-harder-to-open-a-new-asc/)
This is why the strategic question should not be, “Where should we build an ASC?” It should be, “What is the right site of care for our patients, physicians, market, economics, and existing assets?” Sometimes the numbers will point to an ASC. Sometimes they will support an HOPD or continued hospital-based care. Sometimes they will identify an opportunity to reposition an existing asset. And sometimes they may demonstrate that the health system does not need to build anything at all.
The Capacity Left Behind May Be More Valuable Than the Case That Moves
There is another part of the ASC/HOPD business case that deserves far more attention. When appropriate lower-acuity procedures migrate from the hospital to an ASC, the analysis cannot stop with the economics of the case that moved. Leaders also need to understand the value of the hospital capacity that case leaves behind.
If those hospital ORs simply become less utilized, the health system may have changed the site of care without maximizing the enterprise opportunity. If, however, the newly available capacity can accommodate higher-acuity or higher-margin cases, provide access for additional surgeons, support growth in a strategic service line, or recapture procedures currently being delayed or referred elsewhere, the financial equation changes considerably. The organization may be able to grow surgical volume and revenue without adding another hospital OR.
This is why outpatient migration should create a capacity and revenue strategy, not simply a relocation strategy. Leaders need to understand both sides of the equation: what happens economically to the procedure that moves and what new value can be created from the capacity it leaves behind. That is where knowing the numbers becomes critical.
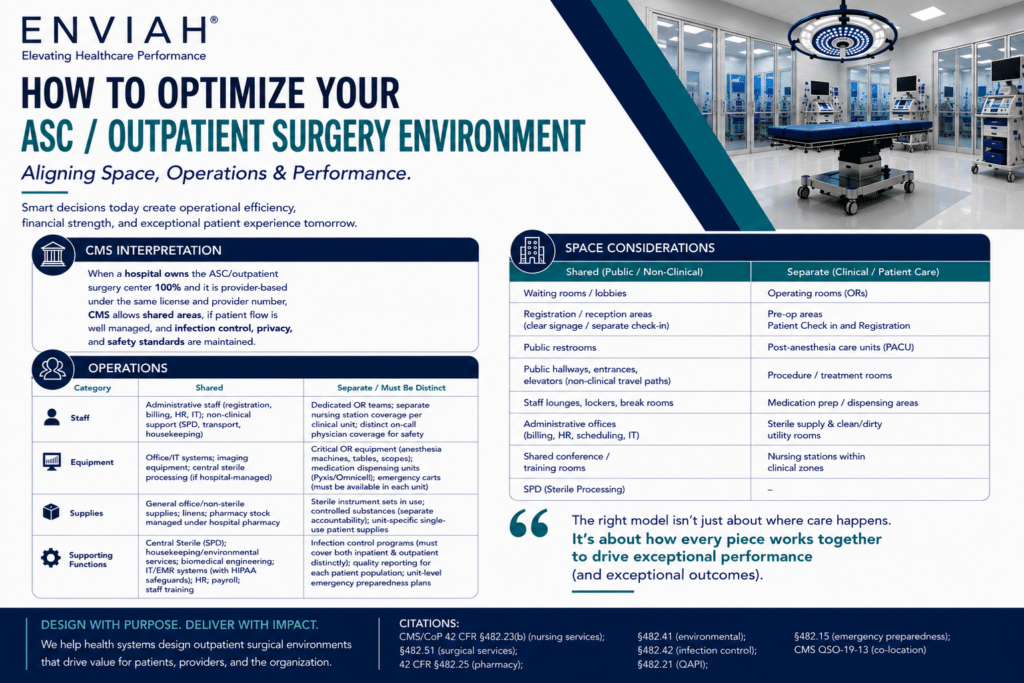
The Second Decision: Make the Entire Surgical Enterprise Perform
Once leaders determine where care should be delivered, the next challenge is making the hospital, HOPD, and ASC work together as one surgical enterprise. This is where an otherwise sound outpatient strategy can become expensive. As new sites are added, organizations can unintentionally duplicate staff, equipment, inventory, sterile processing, pre-op and recovery functions, technology, and support services. Some duplication is necessary for safety, quality, and operational performance, but some simply adds cost.
This is particularly important in a workforce-constrained environment. ASC leaders are reporting shortages of skilled nurses, scrub technicians, and anesthesia professionals, and the migration of more complex procedures into ambulatory settings can increase the need for specialized talent. (https://www.beckersasc.com/anesthesia/is-the-anesthesia-shortage-now-the-real-limit-on-asc-growth/)
A new OR is not meaningful capacity if there are no people to operate it. Likewise, building a second staffing structure for a new site while the organization struggles to staff its existing surgical environments can undermine the economics of the entire strategy. Instead, leaders need to understand where teams can flex between settings, where specialized expertise can support multiple sites, and how schedules can be coordinated around demand rather than around individual buildings.
The same analysis applies to equipment, supplies, sterile processing, and other support services. Expensive equipment does not necessarily need to be duplicated simply because care is delivered in two locations. Inventory may be standardized or consolidated. Certain support functions may serve multiple environments. Other resources may need to remain dedicated because transportation time, turnaround requirements, reliability, or peak demand make sharing operationally impractical.
The goal, therefore, is not to maximize sharing. It is to optimize the use of resources across the system.
Physical Space Determines Whether Sharing Actually Works
This is where the physical environment becomes an important part of the financial and operating model. A shared resource may appear efficient on a spreadsheet but perform very differently once distance, travel time, handoffs, transportation, and workflow are considered.
Centralized sterile processing may reduce duplication, for example, but the savings can quickly erode if instrument transportation delays turnover. Shared equipment may reduce capital expense but create lost OR time if it is not available where and when it is needed. Centralized supplies may reduce inventory and square footage while simultaneously increasing staff walking and retrieval time.
Every one of those movements has a cost. Staff time has a cost. Delayed cases have a cost. Idle equipment has a cost. Underutilized rooms have a cost. And duplicated resources have a cost.
The lowest-cost building is not necessarily the lowest-cost operating model. The right answer comes from understanding how people, processes, technology, equipment, and physical space interact as one system.
That becomes even more important as regulatory oversight evolves. In June 2026, CMS finalized new requirements strengthening oversight of accrediting organizations, including greater performance monitoring, closer alignment with state survey practices, and new provisions addressing potential conflicts of interest. An industry expert described the changes as a potential “wake-up call” for organizations that rely on survey preparation rather than maintaining continuous compliance. (https://ascnews.com/2026/06/new-rules-for-accrediting-organizations-could-impact-ascs-other-providers/)
Compliance, however, should be the floor. A facility can meet code, achieve accreditation, and satisfy its functional program while still operating inefficiently. Performance has to be the goal.
Know the Numbers Before You Build—or Duplicate
Healthcare has traditionally responded to growth by adding physical capacity. Volumes increase, capacity appears constrained, and another OR, HOPD, or ASC enters the capital plan. But a perceived capacity problem may actually be a scheduling problem, a staffing constraint, an inefficient turnover process, a sterile processing bottleneck, an equipment distribution problem, or a physical environment that creates unnecessary movement and delays.
Before adding capacity, health systems need to know what is actually constraining performance and what the existing system could produce if those constraints were removed. Data, AI, analytics, and rapid simulation can increasingly help leaders test those scenarios before committing significant capital. Organizations can model what happens when cases migrate, when higher-acuity cases backfill hospital ORs, when staff flex between locations, when equipment is shared rather than duplicated, when turnover improves, or when existing physical space is repurposed.
The objective is to understand which combination of site of care, staffing, operations, resources, and physical environment produces the greatest throughput, contribution margin, revenue, and capacity from the assets the organization already owns.
That changes the traditional planning sequence. Instead of moving directly from demand to program to building, leaders can move from demand to data to site of care to existing capacity to operating model to physical environment—and only then to capital investment.
The Real Opportunity Is Enterprise Performance
The ASC/HOPD conversation should not end with deciding where to put the cases. That is only the first decision. The larger leadership opportunity is determining how that site-of-care shift can make the entire surgical enterprise perform better.
Health systems need to know which cases belong where, how much capacity already exists, what should replace the cases that migrate, which resources should be shared, which need to remain dedicated, and where workforce, workflow, equipment, or physical space is constraining performance. Most importantly, they need to understand what those decisions mean for throughput, margin, revenue, and capital.
At Enviah, we help healthcare leaders connect operational, clinical, market, financial, and spatial data to understand where capacity exists, where performance is being lost, and how existing resources can be optimized before significant new capital is committed.
Choose the right model. Make the models work together. Get more throughput and revenue from the resources you already own. Then build only what the numbers prove you need.
-

International Well Building Institute Research Advisory
|
An introduction to my journey as an IWBI Research Advisor: Creating a global research agenda focusing on health, well-being, and the built environment. I must begin with how honored I am to work alongside global research leaders at the International WELL Building Institute (IWBI) along with an esteemed team of applied research practitioners from around… READ MORE
-

Designed to Care
|
Scott Kashman, FACHE, Lorissa MacAllister, PhD, AIA, NCARB and Michael J. Markel Jr., RN, FACHE published an article in the Healthcare Executive’s magazine. As health systems continue to be strained by the demands of staffing issues, considering the effectiveness of the environment that surrounds staff is vital. A curated environment that supports teamwork, reflects the organization’s culture and provides… READ MORE
-

Listen to Lorissa MacAllister as a guest speaker on Mary Free Bed Rehabilitation Hospital’s “Be Advised” Podcast.
|
In Mary Free Bed Rehabilitation Hospital’s newest episode of “Be Advised,” host Joyal Pavey talks with Lorissa MacAllister, president and founder of Enviah, a health care design firm. She shares how removing barriers can improve staff success and patient satisfaction. Mary Free Bed CEO Kent Riddle joins the podcast to discuss how Enviah assisted Mary Free… READ MORE
-

Delivering Next-Generation Healthcare- partnering with AECOM on the Henry Ford Macomb Hospital project
|
A Three Step Approach To Improving Healthcare Environments. Using Enviah’s evidence led three-dimensional process – Discover, Design and Do – Enviah collaborated with HFMH in the pre-planning stage. The approach was centered around a thorough investigation and understanding of the Henry Ford Macomb Hospital’s existing operational model and how the new building could transform their… READ MORE
-

Data-Driven Operational Planning
|
What is your facility’s user experience scores; are they identified by location? Do you know how your spaces are performing (productivity, safety and others)? Is the environment designed to reduce harm? What is its highest harm issue? What is the facility’s needs to support another surge experience? Does the environment support a culture of continual… READ MORE
-

Designing Your “New Normal” Work Culture: Using the Return to the Office as a Catalyst for Change
|
Dr. Lorissa MacAllister recently published her latest Studying Spaces column “Resetting for post-pandemic occupancies” in Health Facilities Management Magazine detailing how to set your return to the office up for success. To dig into the topic a little deeper, we are sharing some key takeaways to keep in mind when returning to the office, and why they matter for your… READ MORE